Disc herniations occur when there is a rupture of the outer disc covering, allowing the inner portion to squeeze out, compressing your spinal cord or nerves in and around your spinal canal.
Discs are the soft cushions that act as shock absorbers between your vertebrae. They consist of a soft central portion (nucleus pulposus) and a harder outer covering (annulus fibrosis). These herniations can occur acutely from a specific event or can develop slowly over time, and can occur throughout the spine (cervical, thoracic, or lumbar).
Symptoms
Symptoms can vary from neck or back pain to shooting pain, numbness, or weakness in the arms or legs. A lumbar herniation pressing on a nerve root causes sciatica: sharp, burning, or aching pain that radiates from the buttock down the back or side of the leg, sometimes all the way to the foot. A cervical herniation causes similar radiating symptoms into the shoulder, arm, or hand.
If there is spinal cord compression, patients may experience difficulty with balance, manual dexterity, or controlling bowel or bladder function, among other symptoms.
Pain that stays in the back or neck without radiating into a limb is less typical of a herniation pressing on a nerve, and points toward other sources.
How it is diagnosed
Diagnosis starts with history and physical exam: where the pain travels, which movements provoke it, and whether there is weakness, numbness, or reflex changes in a nerve pattern. MRI is the study that shows the disc itself, the degree of herniation, and which nerve or nerves are compressed. X-ray shows alignment and bone but not the disc. In some cases, EMG/nerve conduction studies help confirm which nerve root is involved, especially when symptoms and imaging do not line up cleanly.
Not every herniation seen on MRI is the cause of pain. Many people have disc bulges or herniations on imaging with no symptoms at all. The exam has to match the picture.
Nonoperative treatment comes first
Most herniated discs improve without surgery. The standard course is activity modification (stay moving, avoid prolonged bed rest), anti-inflammatory medications, physical therapy focused on extension-based exercises and core stability, and sometimes epidural steroid injections to calm nerve inflammation. Many herniations shrink on their own over weeks to months as the body resorbs the extruded fragment.
A reasonable expectation: noticeable improvement over 6 to 12 weeks with consistent nonoperative care. Lack of progress, worsening symptoms, or new weakness changes the plan.
When surgery is considered
Surgery enters the conversation when leg or arm pain persists despite good nonoperative care, typically after 6 to 12 weeks, or sooner when there is progressive weakness, severe pain that does not respond to conservative measures, or cauda equina syndrome (see below), which is a surgical emergency.
The goal of surgery for a herniation is straightforward: remove the fragment pressing on the nerve. Fusion is usually not needed for a straightforward herniation.
Surgical options
For a lumbar herniation causing sciatica, the standard operation is a microdiscectomy: through a small incision, the herniated fragment is removed and the nerve is freed. It is a decompression, not a fusion, and most patients go home the same day.
For a cervical herniation, options include ACDF (anterior cervical discectomy and fusion) or cervical disc replacement, depending on the level, the anatomy, and whether there is instability or arthritis at neighboring levels.
These are minimally invasive or small-incision procedures in appropriate candidates. The full details, candidacy criteria, and recovery timelines are on each treatment page.
Red flags: seek urgent care
Go to the ER or call your surgeon immediately if you develop:
New loss of bowel or bladder control, or numbness in the saddle area (inner thighs, groin, buttocks), which can signal cauda equina syndrome, a surgical emergency
Rapidly worsening weakness: new inability to lift the foot, grip, or bear weight
Severe, unrelenting pain that does not respond to rest or medication
FAQs
Will a herniated disc heal on its own? Often, yes. The body can resorb herniated disc material over time, and most patients improve with nonoperative care within weeks to months. "Healed" usually means the pain resolves and function returns, even if follow-up imaging still shows some disc abnormality.
Do I need an MRI right away? Not always. In the first few weeks of typical sciatica without red flags, the initial treatment is the same with or without an MRI. Imaging becomes important when symptoms persist, worsen, or when surgery is being considered, so the surgeon can see exactly what is pressing on what.
Are epidural steroid injections a cure? They are a treatment for pain and inflammation, not a repair of the disc. For many patients they provide enough relief to get through the healing window and complete rehab. They do not change the long-term outcome compared with time and rehab alone, but they can make the wait far more tolerable.
Will I need a fusion for a herniated disc? Usually not. A straightforward herniation is treated with decompression alone (microdiscectomy in the lumbar spine). Fusion enters the picture when there is instability, a recurrent herniation with back pain from a collapsed disc, or significant spondylolisthesis at the same level.
Can the disc herniate again after surgery? Yes, recurrent herniation at the same level happens in a minority of patients. The risk is higher with larger annular defects and in the early months before the annulus scars down. Activity restrictions after microdiscectomy exist largely to protect that healing.
What about chiropractic care or traction? Some patients get short-term relief from manual therapy or traction. There is no strong evidence they change the natural history of a herniation. Aggressive manipulation in the presence of progressive weakness or cord compression is not advisable. If you try it and symptoms worsen, stop and get reevaluated.
Considering care in Naples
A herniated disc is common, and most cases resolve without an operation. The decision for surgery is based on your symptoms, your exam, and your imaging together, not on the MRI alone. If you have persistent sciatica or arm pain that is not improving, bring your MRI and your questions to HSS at NCH in Naples. A careful exam and imaging review determine whether nonoperative care, an injection, or surgery fits your problem.
This page is educational and not medical advice for your specific condition.
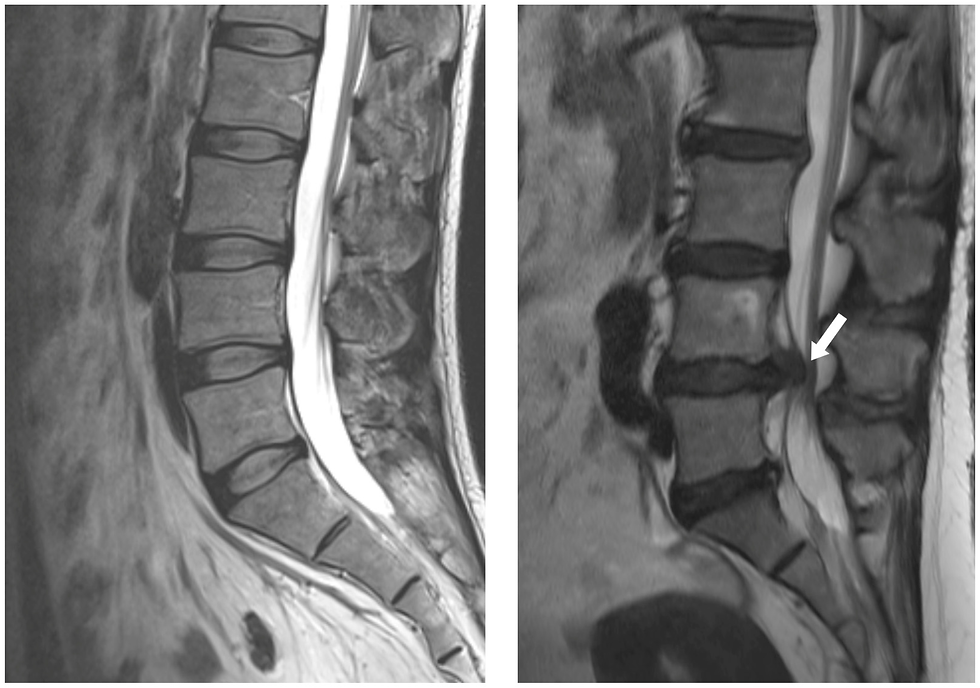
Herniated Disc (Sciatica)
A ruptured disc that presses on spinal nerves, causing pain, numbness, or weakness, potentially requiring surgery if severe.